
Simplified IBD US Severity Assessment
Based on bowel wall thickness, Doppler activity, wall stratification, inflammatory fat, and complication features.
Ultrasound Findings
Bowel wall thickness
Measure the most abnormal segment perpendicular to the wall
mm
Doppler activity
Higher vascularity supports active inflammation
Wall stratification
Loss of layering suggests deeper inflammation
Inflammatory fat / fat wrapping
Hyperechoic mesenteric fat adjacent to the involved segment
Mesenteric lymph nodes
Complication features
Stricture, fistula, abscess, phlegmon, or marked prestenotic dilation
Severity Reference
| Feature | Mild | Moderate | Severe |
|---|---|---|---|
| BWT | >3–4 mm | Thicker | Very thick |
| Doppler | None / minimal | Focal | Diffuse ± mesenteric |
| Stratification | Preserved | Partial loss | Complete loss |
| Fat | None | Mild | Marked |
Bowel Wall Thickness
Mild>3–4 mm
ModerateThicker
SevereVery thick
Doppler
MildNone / minimal
ModerateFocal
SevereDiffuse ± mesenteric
Wall Stratification
MildPreserved
ModeratePartial loss
SevereComplete loss
Inflammatory Fat
MildNone
ModerateMild
SevereMarked
How to do it
- Fasting ~6–8 hrs (optional but improves views)
- Supine positioning
- Use curvilinear (deep) + linear (high-res) probes
- Scan systematically: terminal ileum → proximally or full abdominal sweep
What you measure
- Bowel wall thickness (BWT)
- Doppler vascularity
- Wall stratification
- Peristalsis + compressibility
- Luminal narrowing / dilation
- Extramural findings (fat, nodes, abscess)
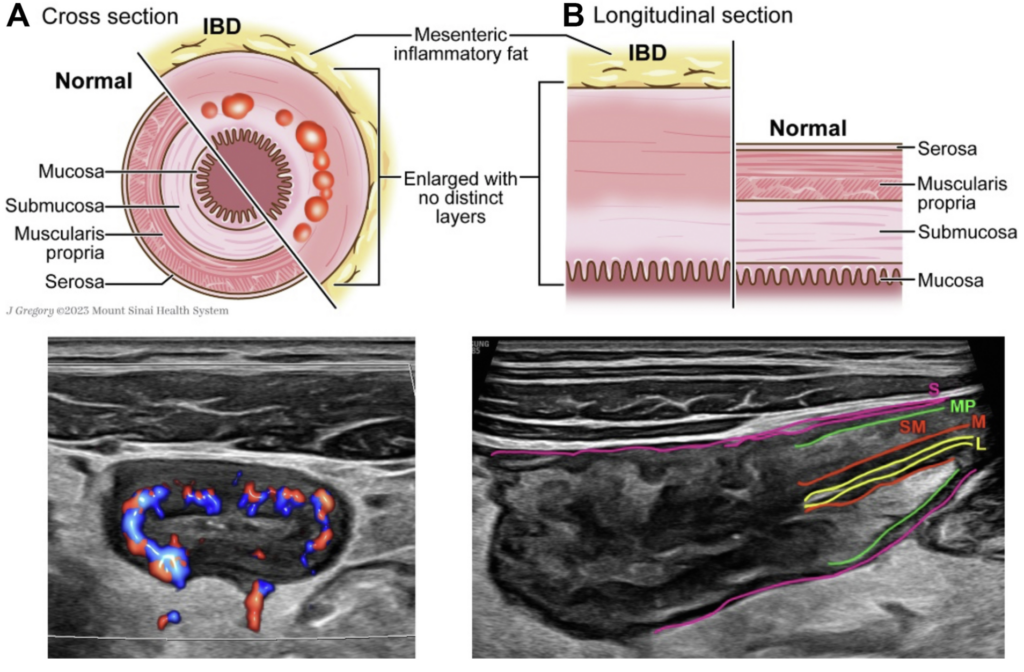
Bowel wall layers
- Mucosa → submucosa → muscularis → serosa
Bowel wall thickness
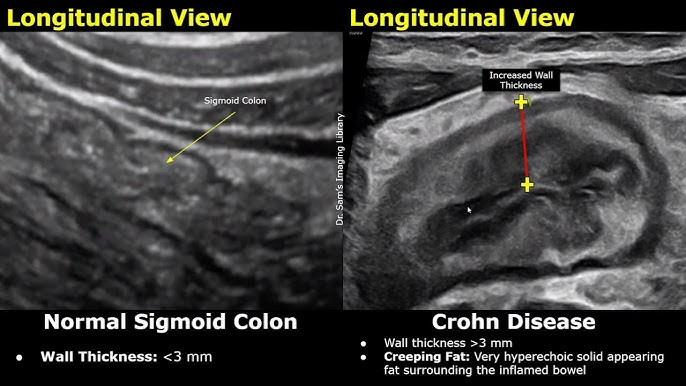
- Measure perpendicular to wall
- Longitudinal + transverse views
- Use most abnormal segment
- Normal: <3 mm
- Active inflammation: ≥3 mm
Doppler grading (Limberg)
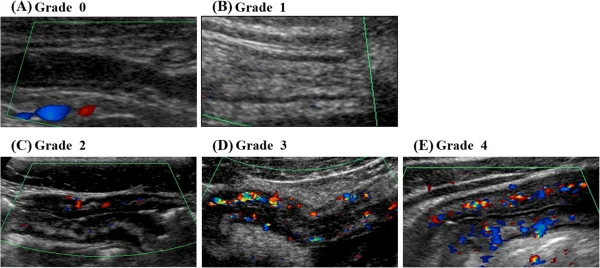
In general ≥2 = active inflammation
- 0 → no flow
- 1 → thickened wall, no flow
- 2 → spotty flow
- 3 → diffuse intramural flow
- 4 → flow into mesentery
Bowel wall stratification (BWS)
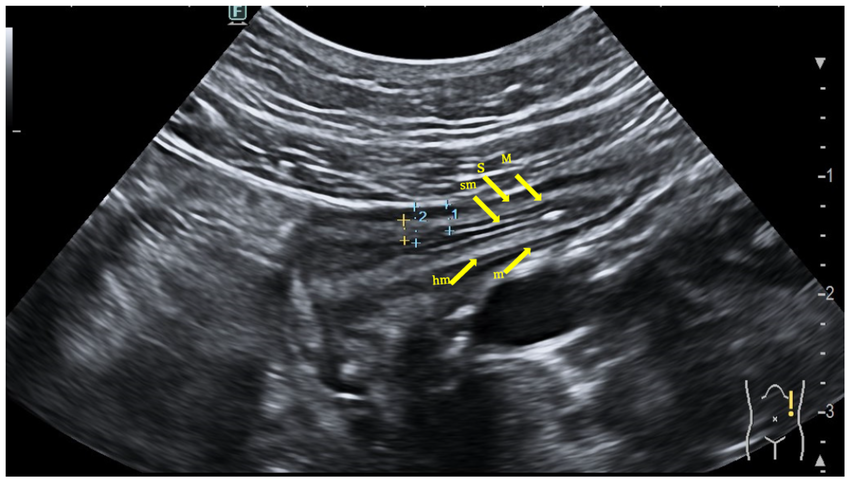
Loss of stratification = deeper, transmural inflammation
- 0 → normal (clear layered pattern)
- 1 → uncertain
- 2 → focal loss ≤3 cm
- 3 → extensive loss >3 cm
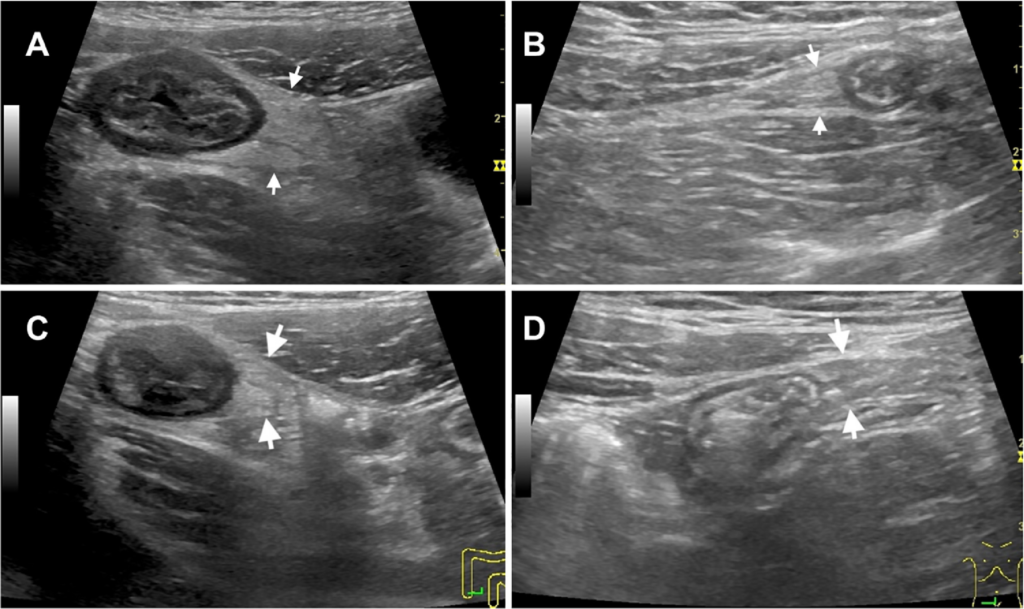
Inflammatory fat (i-fat)
Mesenteric fat hypertrophy adjacent to inflamed bowel (“creeping fat”). Appears hyperechoic surrounding affected segment. It is a marker of transmural inflammation and more common in Crohn's disease. Associated with stricturing and penetrating disease.
- 0 → absent
- 1 → uncertain
- 2 → present
Features of active disease
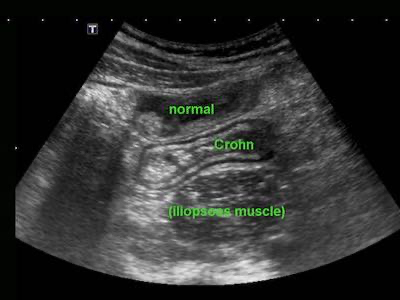
- BWT ≥3 mm
- Increased Doppler signal
- Loss of wall stratification
- Inflammatory fat (creeping fat)
- Mesenteric lymph nodes
Validated Scoring Systems
Ulcerative Colitis
- Milan Ultrasound Criteria (MUC)
- MUC = 1.4 × BWT + 2 × Doppler
- >6.2 → active disease
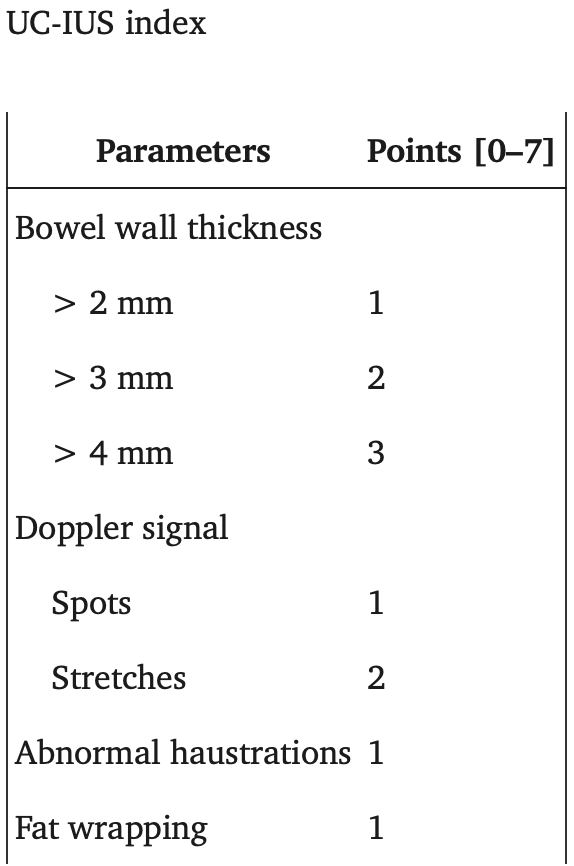
- UC-IUS index (0-7)
- BWT
- Doppler
- Haustration
- Fat
Crohn’s disease
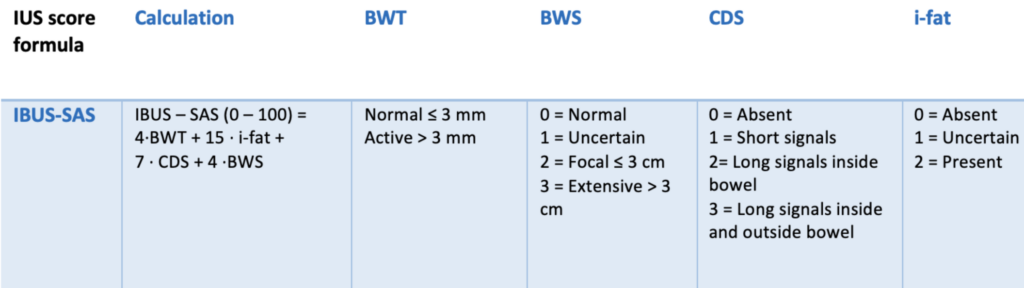
- IBUS-SAS
- BWT
- BWS
- CDS
- I-fat
References
- Kucharzik, T., Tielbeek, J., Carter, D., Taylor, S. A., Tolan, D., Wilkens, R., Bryant, R. V., Maconi, G., Maaser, C., Panes, J., Rimola, J., Rieder, F., & Sturm, A. (2025). ECCO-ESGAR-ESP-IBUS guideline on diagnostics and monitoring of inflammatory bowel disease. Journal of Crohn’s and Colitis. https://doi.org/10.1093/ecco-jcc/jjaf106
- Maaser, C., Sturm, A., Vavricka, S. R., Kucharzik, T., Fiorino, G., Annese, V., Calabrese, E., Baumgart, D. C., Bettenworth, D., Borralho Nunes, P., Burisch, J., Castiglione, F., Eliakim, R., Ellul, P., González-Lama, Y., Gordon, H., Halligan, S., Katsanos, K., Kopylov, U., ... Stoker, J. (2019). ECCO-ESGAR guideline for diagnostic assessment in IBD part 1: Initial diagnosis, monitoring of known IBD, detection of complications. Journal of Crohn’s and Colitis, 13(2), 144–164. https://doi.org/10.1093/ecco-jcc/jjy113
- Novak, K. L., Nylund, K., Maaser, C., Petersen, F., Kucharzik, T., Lu, C., Allocca, M., Maconi, G., Panaccione, R., Ghosh, S., & Wilkens, R. (2021). Expert consensus on optimal acquisition and development of the International Bowel Ultrasound Segmental Activity Score [IBUS-SAS]: A reliability and inter-rater variability study on intestinal ultrasonography in Crohn’s disease. Journal of Crohn’s and Colitis, 15(4), 609–616. https://doi.org/10.1093/ecco-jcc/jjaa216
- Bots, S., Nylund, K., Löwenberg, M., & Gecse, K. B. (2021). Intestinal ultrasound to assess disease activity in ulcerative colitis: Development of a novel UC-ultrasound index. Journal of Crohn’s and Colitis, 15(8), 1264–1271. https://doi.org/10.1093/ecco-jcc/jjab002
- Allocca, M., Filippi, E., Costantino, A., Bonovas, S., Fiorino, G., Furfaro, F., Peyrin-Biroulet, L., & Danese, S. (2021). Milan ultrasound criteria are accurate in assessing disease activity in ulcerative colitis: External validation. United European Gastroenterology Journal, 9(4), 438–442. https://doi.org/10.1177/2050640620980203
- Maaser, C., Petersen, F., Helwig, U., Fischer, I., Roessler, A., Rath, S., Lang, D., Kucharzik, T., & German IBD Study Group. (2020). Intestinal ultrasound for monitoring therapeutic response in patients with ulcerative colitis: Results from the TRUST&UC study. Gut, 69(9), 1629–1636. https://doi.org/10.1136/gutjnl-2019-319451