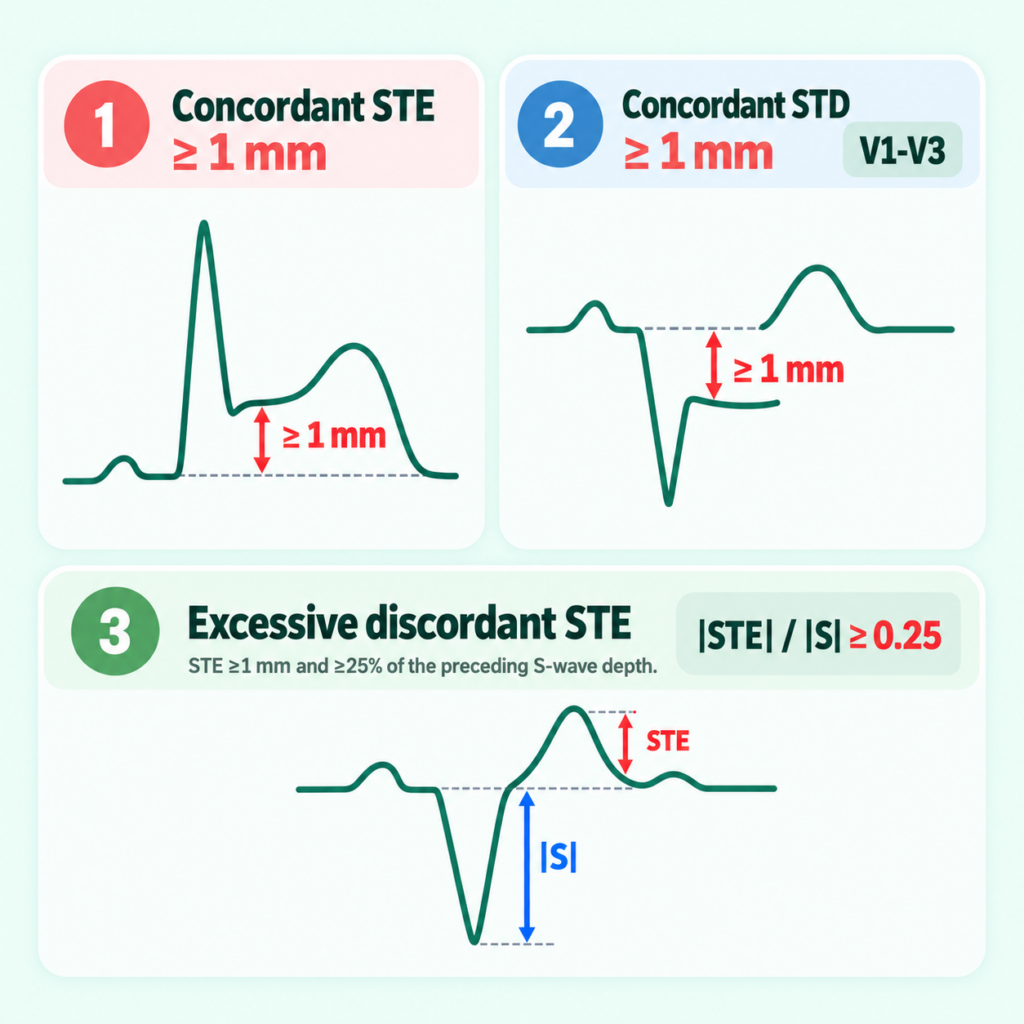
ACS in LBBB: Smith-Modified Sgarbossa Criteria

EKG Lead & Coronary Map Interactive lead orientation, coronary territories & vessel correlates

Lead orientation

aVR aVL I II aVF III RA LA RV LV V1 V2 V3 V4 V5 V6
EKG lead orientation

Coronary territories

Coronary anatomy select a vessel
RV LV LAD D1 LCx RCA PDA PDA = posterior
12-lead territory map
Posterior leads same horizontal plane as V6
Coronary territory map

Smith-Modified Sgarbossa Criteria

1

Concordant ST Elevation

Is there ≥1 mm ST elevation in any lead where the QRS is predominantly positive?

Concordant = the ST segment moves in the same direction as the main QRS deflection. Even 1 mm is positive.
2

Concordant ST Depression

Is there ≥1 mm ST depression in V1–V3?

In the standard Smith-modified rule, ≥1 mm concordant ST depression in V1–V3 is positive.
3

Excessively Discordant ST Elevation

Is there discordant ST elevation in a lead with a predominantly negative QRS?

mm
mm
Enter both measurements. Use the absolute depth of the S wave.
—
0% 25% threshold 50%+
Modified criterion: discordant STE must be ≥1 mm and at least 25% of the preceding S-wave depth. Example: S wave 12 mm deep → STE ≥3 mm is positive.

Criterion 1
Concordant STE ≥1 mm
Any lead with a predominantly positive QRS.
Criterion 2
Concordant STD ≥1 mm
Present in at least one of V1–V3.
Criterion 3
Excessive discordant STE
STE ≥1 mm and ≥25% of the preceding S-wave depth.
|STE| / |S| ≥ 0.25

Measure the lead with discordant ST elevation

  1. Measure ST elevation at the J point relative to the PR-segment baseline.
  2. Measure the absolute depth of the preceding S wave.
  3. Divide STE by S-wave depth.
  4. Positive when STE is ≥1 mm and the ratio is ≥0.25.
Example: STE 3 mm ÷ S wave 10 mm = 0.30 → positive
S-wave depth STE J point STE ÷ |S| ≥ 0.25

  • Any 1 criterion is positive. The modified rule is unweighted.
  • Positive criteria are highly concerning for acute coronary occlusion when the clinical presentation is compatible and should accelerate an emergent reperfusion evaluation.
  • Do not use a negative result to rule out OMI. Serial EKGs, symptoms, troponin trajectory, bedside echo, and angiography may still be needed.
  • Best studied in LBBB. Modified Sgarbossa also performs better than the original criteria in ventricular paced rhythm.
LBBB validation
80% sensitivity · 99% specificity
For acute coronary occlusion in the 2015 retrospective validation study.
Ventricular paced rhythm
81% sensitivity · 96% specificity
Against the no-OMI control group in a 2021 multicenter study.

  • Do not use the old 5 mm discordant STE cutoff. Large-voltage LBBB can produce >5 mm of normal discordance.
  • Use the absolute S-wave depth when calculating the intuitive STE/S ratio. The original research expresses the negative S wave mathematically, so the published ST/S cutoff is ≤ −0.25.
  • Measure at the J point relative to the PR-segment baseline. Small measurement errors matter near the 0.25 threshold.
  • Look at every lead. Criterion 3 can occur anywhere; criterion 2 is specifically V1–V3 in the standard modified rule.

Smith-Modified Sgarbossa Digital Calipers

Uploaded EKG tracing
No image loaded
1.0×
Upload an EKG image to start. Green crosshairs and the magnifier are on by default.
Vertical grid calibrationUpload an imageNot calibrated
The tool will try to auto-detect one 5 mm large box. Verify it with the 5 mm guide. If detection misses, click two horizontal gridlines that are the selected distance apart. Use the same lead and image scale for all voltage measurements. Standard gain: 10 mm/mV.
1Concordant ST elevationNot reviewed

In any lead with a predominantly positive QRS, measure upward J-point displacement from the isoelectric baseline. Criterion positive at ≥1 mm.

No leads measured.
2Concordant ST depressionNot reviewed

In V1–V3 with a predominantly negative QRS, measure downward J-point displacement. Criterion positive at ≥1 mm.

No leads measured.
3Excessively discordant ST elevationNot reviewed

In a lead with a predominantly negative QRS and discordant STE, complete two measurements in the same lead and beat: 1. Click the TP baseline, then the preceding S-wave nadir. 2. The TP baseline stays locked. Click only the J point above it. The tool calculates STE ÷ absolute S depth × 100. Positive when STE is ≥1 mm and the ratio is ≥25%.

No discordant leads measured.
References
1
Smith SW, Dodd KW, Henry TD, Dvorak DM, Pearce LA. Diagnosis of ST-elevation myocardial infarction in the presence of left bundle branch block with the ST-elevation to S-wave ratio in a modified Sgarbossa rule. Ann Emerg Med. 2012;60(6):766-776.
View derivation study
Derivation
2
Meyers HP, Limkakeng AT Jr, Jaffa EJ, et al. Validation of the modified Sgarbossa criteria for acute coronary occlusion in the setting of left bundle branch block: a retrospective case-control study. Am Heart J. 2015;170(6):1255-1264.
View validation study
LBBB Validation
3
Dodd KW, Zvosec DL, Hart MA, et al. Electrocardiographic diagnosis of acute coronary occlusion myocardial infarction in ventricular paced rhythm using the modified Sgarbossa criteria. Ann Emerg Med. 2021;78(4):517-529.
View paced-rhythm study
Ventricular Pacing
4
Cadogan M, Buttner R. Sgarbossa Criteria. Life in the Fast Lane ECG Library. Updated February 18, 2025.
View LITFL review
Clinical Review